Bipolar 2 From Inside and Out

Posts tagged ‘depression’

Men, Women, and Mental Health

My husband is no stranger to situational depression. He experienced it when his father died, when a beloved pet passed unexpectedly, and when his job turned suddenly more stressful and meaningless.

But he didn’t understand clinical, chronic depression. “What would it be like if those feelings lasted for months at a time, or even years?” I asked. He said he couldn’t even picture it. “That’s the way my life is,” I explained. Then he lost his job, and after a brief period of relief from the stress, he finally experienced depression that lasted more than two weeks – two years, in fact, during which he was unable to work.

He did not seek help for it until his best friend and I both proactively encouraged (i.e., nagged) him to do something about it. He’s been on an SSRI ever since and has occasionally seen a psychologist.

Lately, there has been a movement to educate men about mental illness and mental health. Primary among its goals is to help men understand that mental illness is a thing that can affect them and that there is no shame in asking for help.

Certainly, the statistics bear out that the majority of mental health consumers are women. Psychology Today reports: “Research suggests that women are about 40% more likely than men to develop depression. They’re twice as likely to develop PTSD, with about 10% of women developing the condition after a traumatic event, compared to just 4% of men. It’s easy to write off this epidemic of mental illness among women as the result of hormonal issues and genetic gender differences, or even to argue that women are simply more ’emotional’ than men. The truth, though, is that psychiatrists aren’t really sure why mental illness is more common among women.” Perhaps the answer is that seeking treatment for mental illness is more common in women.

Prevention magazine says that there are four mental health conditions that affect women more than men: depression, anxiety, PTSD, and eating disorders. That PTSD is twice as common in women may surprise you, though the stats about eating disorders are not likely to. The fact is that, although few women experience the traumas that soldiers do, they are much more likely to experience other sorts of trauma, such as rape, which can also lead to PTSD.

But men experience societal and psychological barriers to getting help when they need it. Among the excuses you hear are these:

  • I don’t really need help.
  • I can handle this myself.
  • I don’t want to appear weak.
  • I might lose my job if anyone finds out.

In other words, a lot of bullshit that boils down to “I’m a man and mental illness is not manly. Asking for help is not manly. Talking about emotional problems is not manly. Taking medication for a personal problem is not manly. Not being able to deal with my problems, especially emotional problems, is not manly. Therefore I have no mental problems and don’t need treatment for them because I’m a man.”

Or, looked at another way, the campaigns against stigma around mental illness have been less than effective for most men. Now the attention to that problem, which is surely needed, is beginning to be heard and, one hopes, acted upon.

Still, it’s important to remember that mental illness is not just a men’s problem or a women’s problem. It is a human problem, affecting both genders (and all ages and races) if not equally, then without discriminating.

It is important to get men the mental and emotional help they need, in a timelier and more comprehensive fashion.  I would have liked to see my husband be willing to recognize when he needed to get help and to get it without being pushed. But it would be wrong to push the needs of women aside to accomplish this. This is a societal problem, and while right now spreading the word to men is particularly important, our goal should be to make sure that all people are aware of the prevalence of mental illness, the fact that it can happen to them, and that there are places to get help. That message, at least, is not gender-specific.
My Turn to Care

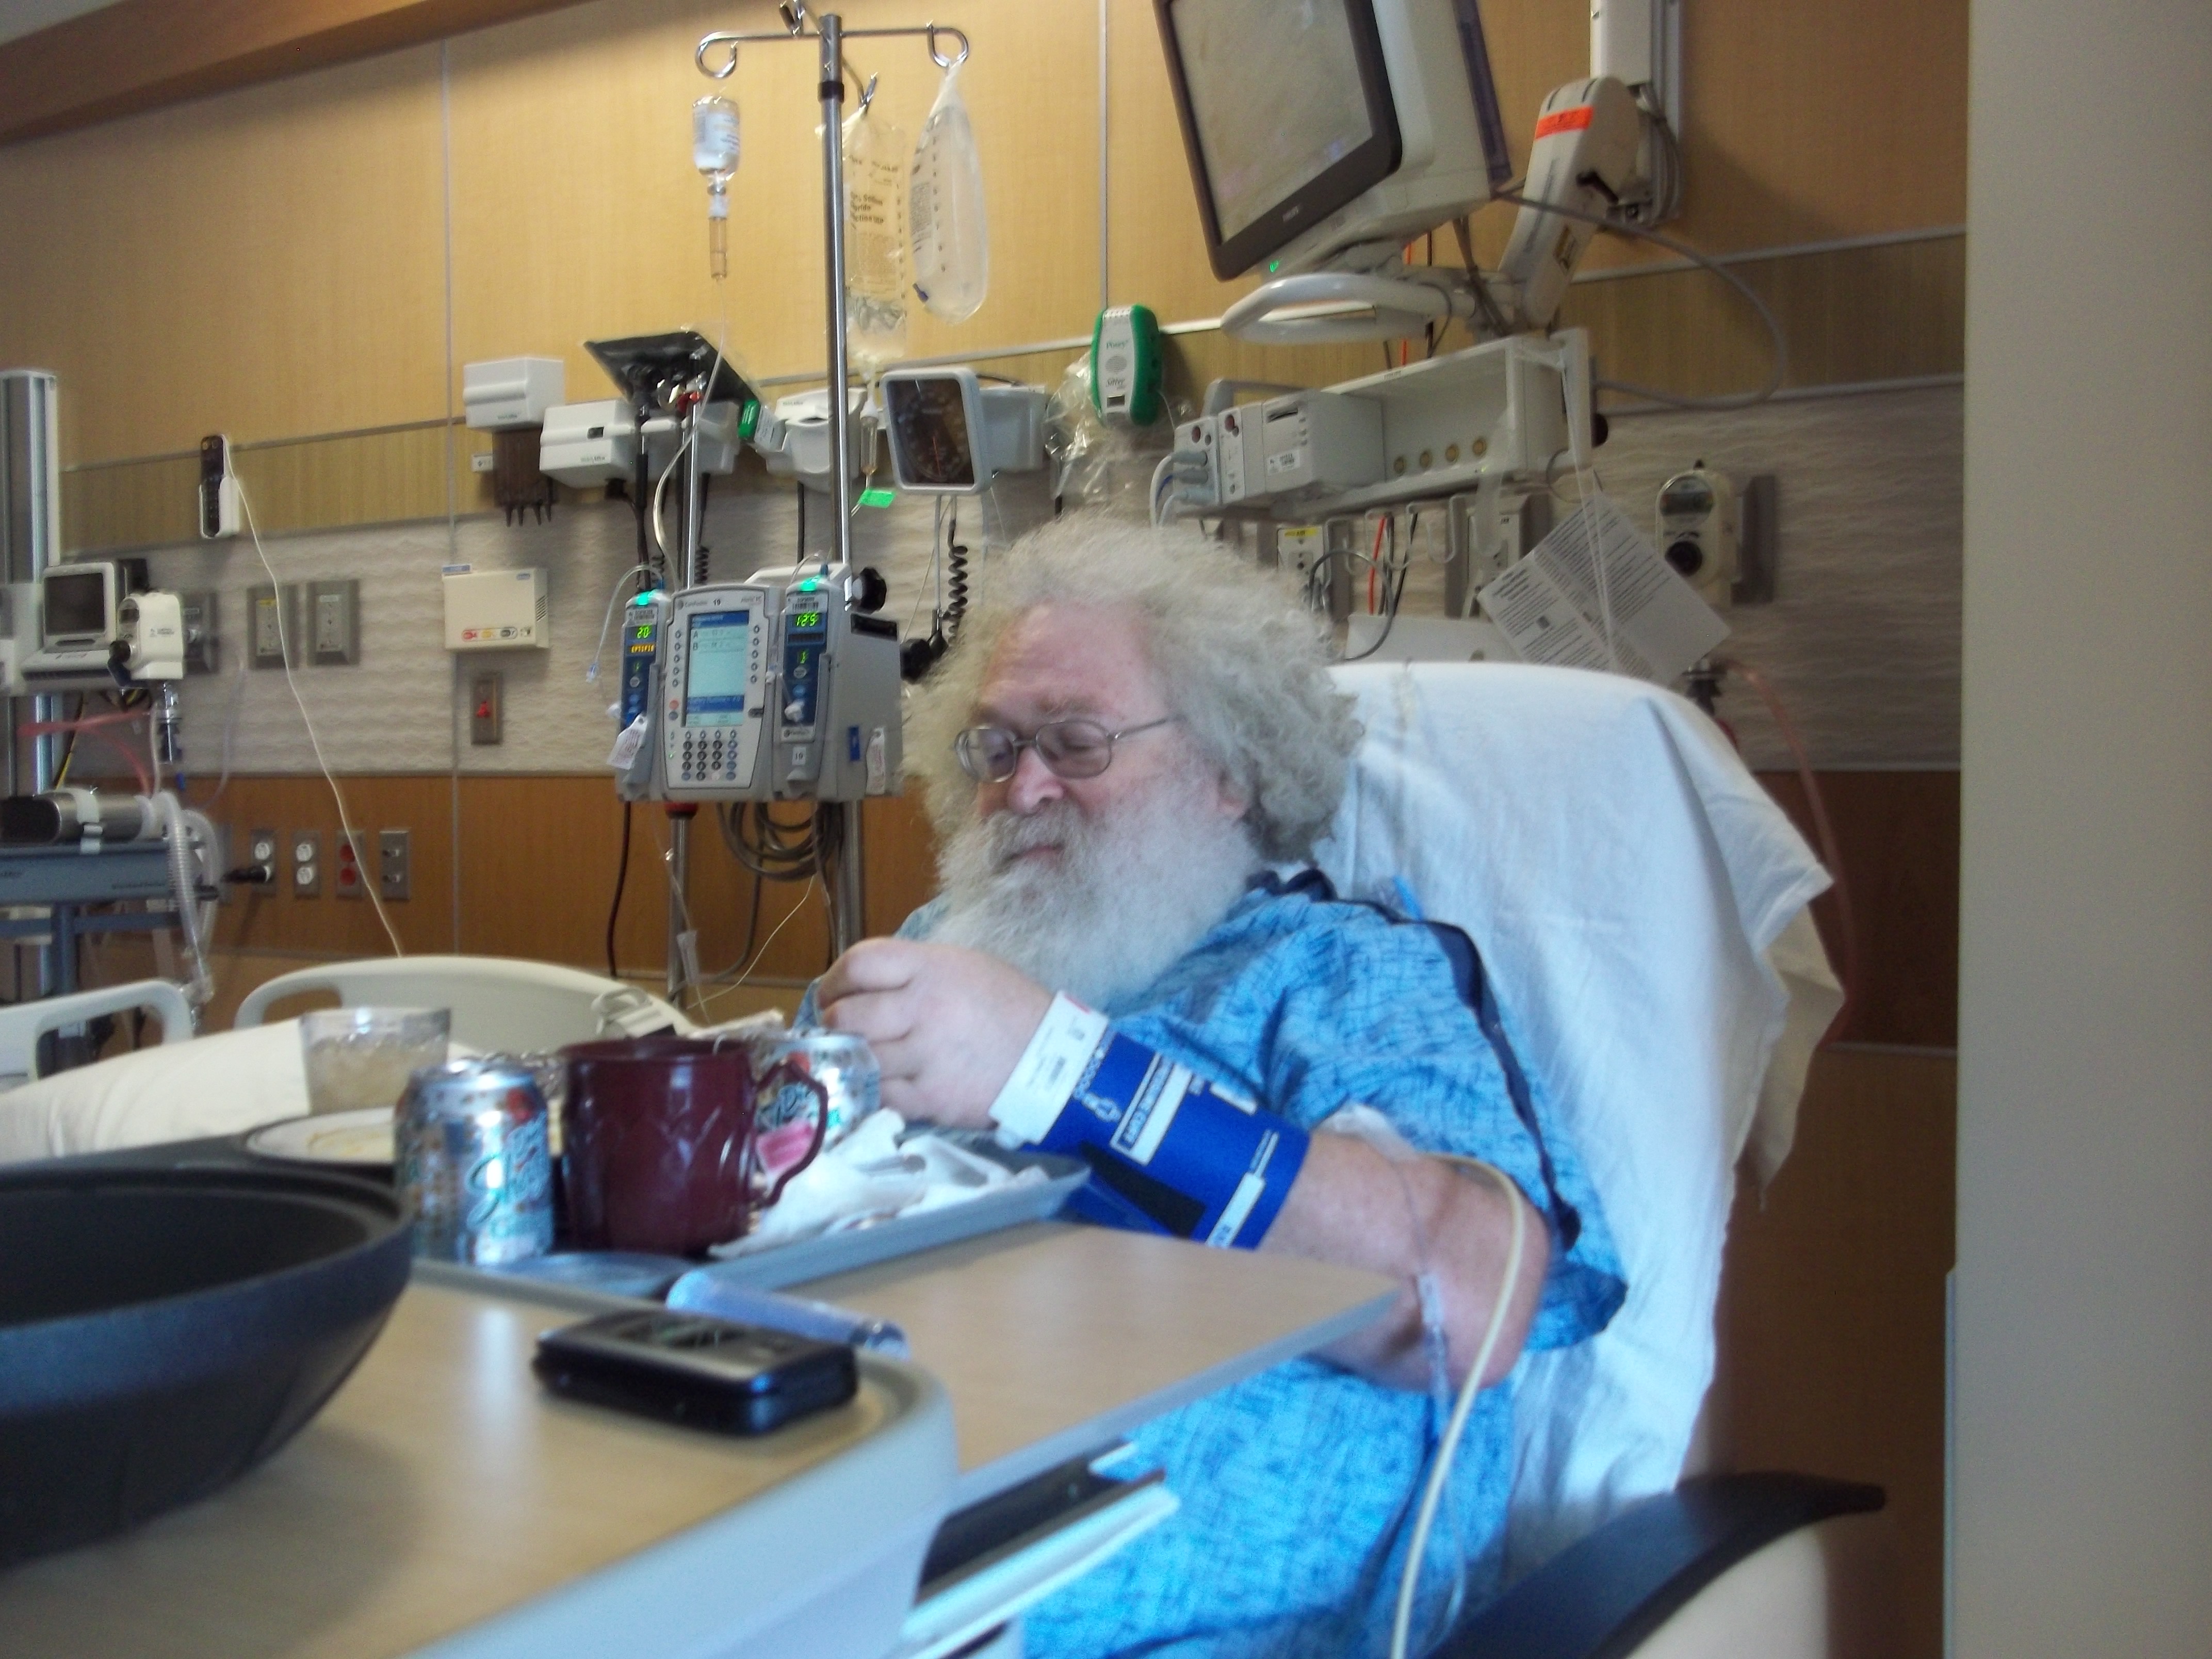
My husband had a heart attack this fall. He got a total of five stents, avoided open heart surgery, and is now in cardiac rehab. And I am helping take care of him.

Dan has been my caregiver as long as I’ve known him. He has stuck with me through the various ups and downs of bipolar disorder – when I was untreated, when I was struggling with finding the proper medication, when I shouted at him, when I was immobilized – whatever. I couldn’t have got through what I’ve been through without him.

Now I get to pay him back, at least a little, for all he has done for me. I have no training and little experience as a caregiver. But there a few things I can do for him, in addition to loving and supporting him as he has loved and supported me.

I can facilitate his appointments, meds, and procedures. Dan has a tendency to forget when is next appointment is, and with which of his many doctors. I have a perfectly good whiteboard in my study on which I note my own appointments as well as keep track of my work. It’s no trouble at all to add his and remind him.

Getting to his appointments is another area where I can help, especially since his cardiologist has a number of offices in various parts of town and in nearby suburbs where he practices on different days of the week. Since I’ve lived here most of my life, I know the area better than he does and I go with him to navigate. (He’s never gotten used to GPS.) I suggest routes that are easy to retrace and figure out when to leave to get there on time.

Dan has in the past had a habit of forgetting to take his various medications.  When that involved sertraline, I didn’t worry much since I know that once a certain level has built up in the body, missing a dose is not such a big deal. But with his blood thinner, a missed dose could lead to a clogged stent and another heart attack. So I proactively encourage him (as my therapist suggests I call nagging) to take them daily and on time.

I can handle financial stuff. With Dan being off work for so long and hospital and doctor bills adding up, our finances are getting pretty tricky. I can make sure I have steady work and even take on extra sometimes. I can fill out the forms for short-term leave, financial assistance, insurance, and other necessities.

I’ve even been able to set up PayPal and Facebook funding pleas to help us get a little extra cash to pay the utilities and other bills. (GoFundMe may be next once all the medical bills are in.)

I can handle computer stuff. Finding locations of offices and hospitals and the cardiac rehab place, phone numbers of financial aid programs, and names and side effects of medication are easier and quicker for me to do on my Mac than for him to do on his ancient PC. I can find things he needs on ebay for the lowest price. I can find and email various forms and records of expenses to wherever they need to go. This may sound minor, but believe me, it can take up a lot of time and frustration. I think of it under the heading of relieving his stress.

I also know how to network. A Facebook friend of mine teaches Tai Chi at a local Y. Through him I found out that the Y does not charge for his classes. And through Google I found that this month the Y waives membership fees if you donate canned goods to a local food pantry. The Y’s amenities include exercise classes and water aerobics, which I also could use. I also found a local Senior Center that has yoga and free weights (and community theater) as well.

I can understand his depression. Being faced with intimations of one’s mortality, combined with money problems and not being able to work can make anyone depressed. And Dan was already taking meds for depression before this current crisis even started. I am, of course, a third-degree black belt when it comes to depression. I know how he feels, why he’s feeling it, and what will and won’t work in helping him through it. I can be patient, supportive, and there to communicate or simply hug when he needs to, as he has so often done for me.

There’s not much care that my husband needs in the way of actual physical care. He is not so incapacitated that he needs help with feeding, dressing, bathing, or other tasks of daily living (other than changing his bandages when he cut his finger open and required eight stitches).

But I like to think that the support I can give him helps in his recovery by taking some of the stress off him, which his doctor recommends and which he has done for me innumerable times. We’re a team and this time it’s my turn to take some of the weight.

Bipolar Disorder: Mood and Food

anise aroma art bazaar

Photo by Pixabay on Pexels.com

FDA looks to ban trans fats. Exceptions made if consumed while depressed, anxious, or without anything better to do.

The Daily Show

If that were true, I could eat all the trans fats I wanted, because my bipolar 2 often leaves me depressed and/or anxious.

In fact, my friend Leslie, who is my partner in depression, invented the perfect snack for depressive times: a ruffled potato chip dipped in cream cheese with an M&M on top. My husband starts to worry about me when I ask him to get those ingredients at the store.

But there’s a reason for our peculiar snack. Leslie and I are simply self-medicating.

“Blood sugar and carbohydrate intake are very important to the brain,” according to Everyday Health. “Your brain runs on glucose and depends on carbohydrates to supply the energy it needs. Carbohydrate intake also prompts the production and release of important neurotransmitters, such as serotonin, which creates a feeling of calm and well-being and reduces depression. So people with bipolar disorder may be indulging in a form of self-medication when they eat sugary snacks during depressive lows or manic highs.”

Not that self-medication is good for us. Bipolar people are more likely to have type 2 diabetes than the rest of the population. Three times more likely. One of the risk factors for type 2 diabetes is excessive weight and we all know and bitch about the weight gain from our assorted meds. Prescribing ourselves the Ben & Jerry’s treatment is not going to help, even though it may feel like it at the time.

So what are we supposed to be eating to help stabilize our moods? Of course, people will recommend turmeric, cider vinegar, or the latest “superfood.”  But every serious list I saw looked like this:

  • complex carbohydrates, especially fruits, vegetables, and whole grains
  • protein in the form of lean meats, poultry, fish, and low-fat dairy
  • omega-fatty acids from fatty fish (such as salmon), walnuts, and flaxseeds

In other words, exactly the kind of diet that is recommended to everyone for general good health! I think this comes under the heading of self-care, which is not always easy to do. Especially when I’m so depressed I can’t even manage a microwave cup of mac-n-cheese, or when my husband brings home a rack of ribs that he bought on sale.

But if I am stable enough to shop and cook and eat properly, those recommended foods may be good for my mood disorder as well as my body. According to bipolar.newlifeoutlook.com, eating protein “promotes serotonin and improved moods.” They also note that researchers in Italy say “increased consumption of omega fatty acids helps reduce depressive episodes and decreases the risk for suicide in patients with bipolar.” So apparently fish is brain food after all.

The other common suggestion in this realm of self-care is to keep a food journal, or I guess in this case a food and mood journal, to keep track of what you’re eating and how it affects your moods. If you’re the journalling sort, by all means, give this a try. As for me, I blog rather than journal and I know you don’t want to see a lot of “ate salmon, felt energized; ate chips with cream cheese and M&Ms, felt sad.”

The fact that food and mood are related is just one more example of how the brain and the body are intertwined, interdependent. It gives us a clue about the kinds of self-care that may do the most to help us stabilize our moods. And it gives us a chance to take more control, if we can, of our mental as well as physical health.

The Appropriate Committee


blur close up focus gavel

Photo by Pixabay on Pexels.com

When I was a teenager, my life was spent resenting the Appropriate Committee. I always ran afoul of them.

It seemed there was some nebulous group, invisibly judging us and deciding whether what we did, or wore, or how we acted was appropriate or not.

Part of the Appropriate Committee was, of course, the adult world. Teenagers were supposed to be polite and respectful and not talk or play music too loudly. To do otherwise would be inappropriate.

The social milieu was also part of the Appropriate Committee. How we monitored one another to make sure our pants weren’t too short, or that we didn’t wear ankle socks, or that we didn’t stay in the Girl Scouts past Brownies. The punishment was derision.

Of course being bipolar didn’t help. Both adult and junior versions of the Appropriate Committee took note of my mood swings – my loud, inappropriate laughter; my extreme, inappropriate crying; my extended, inappropriate isolation.

I tried to defy the Appropriate Committee. I laughed at them, thought they were stupid, and vowed not to let them run my life. They did anyway, of course. They were all-powerful and I had not yet gained the wherewithal not to care. It was like a pervasive, invasive form of bullying: Everything I did or said was wrong. The rules changed capriciously. I was punished with disapproval, mocking, and the wrong kind of laughter.

And they broke me. At times I tried desperately to fit in, to live up to expectations, to suppress my differences. At other times, when the effort became simply too much, I let my natural weirdness float to the surface and looked for the few other like-minded individuals that could tolerate that. Depression set in and, rarely, hypomania. I still dressed “wrong.” I still laughed at the wrong things, and too loudly. I still isolated and wept.

I thought that when I grew to adulthood, I would no longer be subject to the censure of the Appropriate Committee, Of course, that was completely delusional. I learned that the Appropriate Committee for Adults was a powerful force. It is particularly insidious in the business world, where it judges not just your appearance, but even seemingly minor matters such as where and how you eat lunch (with the “cool kids,” of course) and how you spend your breaks (cigarettes OK, crossword puzzles not). There’s still the problem of being laughed at in meetings and needing to go into the restroom to cry.

I finally realized that the Appropriate Committee exists in part to perpetuate stigma. So many of the behaviors of people with mental illness defy societal norms. It’s the Committee that insists we fit in, no matter what we’re feeling. It’s the reason that neurodivergent people are so reluctant to admit their differences in public and try their best to “play through the pain,” something that isn’t good for them, or for athletes either, really.

I’ve had enough of the Appropriate Committee over the years. Now that I’m properly diagnosed and medicated and relatively stable, I could undoubtedly fit in better than at any time previously in my life. But I dress how I like, even if it’s pajamas. I play my music as loud as I want and laugh or cry along with it if I feel like it. I embrace my weirdness, my differences, and seek out like-minded weird friends who are also living in defiance of the Committee.

Maybe the Appropriate Committee is needed for some places and times and people, like theater audiences or church services. Maybe. But for the mentally ill the Committee is hurtful, and stigmatizing, and unrealistic. We can strive to overcome our differences and sometimes we need to. But sometimes it’s better just to embrace weirdness, differentness, and our membership in the group of the neurodivergent.

And when I despair, I remind myself of songwriter Steve Goodman’s lyric: “I may not be normal, but nobody is.” And I let it blast.

The Golden Glow and the Spoons

art board cooking flowers

Photo by Aphiwat chuangchoem on Pexels.com

Hypomania is as insidious as it is enjoyable.

I remember when I quit my 9–5 office job to go freelance. I remember when I made the decision. I had gotten my first bad review, ever, shortly after disclosing my bipolar disorder to my new boss.

I remember driving around shortly thereafter, running errands in the middle of the day. I felt the warm, golden glow that goes with either happiness or hypomania. I could wake when I pleased and work when I pleased. I could run those errands when I wanted. I could take my mother to her doctor’s appointments whenever I needed to. I could make and go to my own appointments as necessary.

Best of all, I felt as though I had enough spoons to do all this. I was able to keep up with the work and the errands and the appointments and, hey, if I got tired I could take a nap in the middle of the day.

But.

Eventually the glow wore off and the spoons ran out. Hypomania dumped me back into the depression I was oh-so-familiar with. I had more work to do and less energy to do it. My mother’s problems increased and I had to take over her finances as well as my own. I was teetering on the edge of a major depression, and then I fell off that cliff.

Anymore I don’t trust hypomania. First of all, I can’t distinguish it from actual happiness, competence, or satisfaction. I always question its sincerity and watch out of the corner of my eye for the coming crash. In other words, when I’m happy I can’t even enjoy happiness without reservation.

One way I keep track of my hypomania is by being aware of the number of spoons I have. If I’m flying on a hypomanic cloud, I feel replete with spoons. It never occurs to me that I will run out. When I’m experiencing garden-variety happiness, I still suffer at some point from lack of spoons. No matter how many pleasing things are scheduled for the day, I know deep inside that I cannot simply dive into all that bounty. My joy is measured out, as the poet said, in coffee spoons or in this case metaphoric spoons which I always visualize as small white plastic ones.

Stability for me does not mean that I can ignore my supply of spoons, either. I may be on an even keel, able to do most of what I want, but inevitably the spoon depletion hits, sooner or later. There is simply no more that I can do, much as I want to. And if I force myself past that point, I will surely pay for it in exhaustion, irritability, or isolation.

Spoons, therefore, run my life. If I am too happy, I have to watch for incipient spoon depletion.  If I am level, I know that I must still keep track of the spoons I use. And if I am low, my spoons can disappear altogether, to the familiar point of not being able to get out of bed.

I think the trap of hypomania is the worst of all. On a high like that I can lose track of my spoons – even forget that they are necessary. Fortunately, I don’t get the full-blown version of mania. I fear I would squander spoons recklessly, leaving me a terrible absence of any.

Spoons are a useful way to explain the energy demands of chronic and/or mental illnesses. My husband and I speak spoonie shorthand. But I wish I could experience that golden glow, that haze of happiness, that feeling of floating, without having to keep one eye on the spoon-meter.


Bipolar Sex: Drought and Abundance

two people laying on a bed covered with a floral comforter

Photo by rawpixel.com on Pexels.com

Here’s something bipolar people talk about amongst themselves but not so much with the world outside: sex.

The two poles of bipolar, depression and mania, govern a person’s appetite for sex. A lot of other factors determine whether the sex will be any good, or good for the participants.

Of course the above is true for neurotypical people as well. Moods and emotions – things in the brain – have as much or more to do with sex than stuff in the body. Thinking about sex and wanting sex, for example, start in the brain and without them, nothing else is likely to happen anywhere else.

The depression side of bipolar sex is easy enough to map out. After all, some of the hallmarks of depression are numbness, inability to enjoy things that once gave pleasure, and a tendency to isolate. It’s hard to get your motor revving with all that going on.

Still, the depressed person may want to have sex, or at least want to want to. That’s the way it’s been with me. When I’m in a thoroughly depressed state, sex doesn’t even cross my mind. When I’m not quite as depressed, I think I might like to have sex but don’t have the energy for it. And when I’m relatively stable, there’s the meds.

It’s well known that medications for bipolar disorder can kill the sex drive and in men the ability to get or maintain an erection. Some drugs supposedly have less effect on sexuality, but I’ve never found the magic combination. Or the supposed sex-friendly drug has had side effects I can’t tolerate.

So if bipolar depression is largely a big zero for bipolar sex, how about mania?

Overactive sex drive combined with a lack of impulse control can lead to sexual excess. The tendency to minimize risk-taking behaviors means that some of that sex can be detrimental to one’s health, relationships, and self-esteem. Riding that wave is exhilarating, but then, inevitably, comes the crash and the need to pick up the pieces.

Full disclosure here: Since I have bipolar 2 and my hypomania tends to turn sideways and come out as anxiety, I don’t experience that manic sex high. On the whole, I think I am grateful for this. Sex has never been such an important part of my life that I would risk everything for it.

Once, though, I did experience what you might call a hypomanic sex drive. It smoldered for a long time, requited but unconsummated, until the right set of circumstances presented themselves. It was a restlessness, an obsessive thought, a longing for connection, rather than an ungovernable rush of need. It gave me, perhaps, a glimpse of what it might be like to be manic and sexually stimulated. But I’ll never really know.

I do know that I am glad I had the experience, whatever it was. I’m glad it was safe sex.  I’m glad it didn’t destroy relationships. But just to feel that desire again, even if only for a brief time, even with the anxiety it provoked – and there was lots – it was a kind of affirmation that my body and brain are still connected in some vital way.

Most of the time I limp along with only thoughts of sex too fleeting to act upon. And maybe this is not the best way to live, but I have made my peace with it. And once in a great while, every now and then, I still am reminded that I can have a sexual existence.

Even though I have bipolar.

Of course, as always, your mileage may vary.

The Disability Tapdance

man in brown long sleeved button up shirt standing while using gray laptop computer on brown wooden table beside woman in gray long sleeved shirt sitting

Photo by rawpixel.com on Pexels.com

Once I applied for disability for my bipolar disorder and I was turned down Then I took the process as far as I could with a lawyer and he eventually advised me to give it up too. Here’s my story.

I had gotten to the end of my proverbial rope and we had gotten to the end of our money. For over a year I had been sidelined by unremitting depression. There was nothing I could do and nothing my psychiatrist prescribed or my therapist said had helped. We had been living on my husband’s salary and what was in my 401K from when I had last been able to work.

At last my husband pointed out that we couldn’t hold out much longer. He encouraged me to apply for disability. I knew that there would be lots of hoops to jump through and that there was no guarantee of succeeding. But Dan was willing to go with me to the Federal Building and help me get through it. I certainly wasn’t capable of managing it on my own.

Between the two of us, we had looked up what sorts of documents I would need and had acquired them. I was glad we were able to do this because going back again and again for missing documents would have been a horror. I had my appointment with the intake person and went back home to wait.

There were more forms to come. My psychiatrist had to fill out a long one, of course, or write a letter, I don’t remember which. I had to pay him for his time and trouble in doing that but at that point it was just another step that needed taking.

The big step was the psychological interview where I had to perform my little song and dance and convince someone that I was truly disabled. Fortunately, the appointment was not downtown in the Federal Building but in a relatively nearby office building that I knew how to find. Then the hoop-jumping and tap dancing really began.

They tested my memory. They told convoluted stories and asked me questions about them such as the order in which things happened and why the characters did what they did. They were confusing.

They tested my spatial perception. They had me put together those cubes with triangles on them to match patterns they showed me. I still don’t know what that had to do with bipolar disorder.

Then came factual knowledge. I was good at that one. I admit I guessed when they asked me how big around the equator was. I knew the easy stuff like who wrote Tom Sawyer and such.

By the time they got to the word association test, I was very tired. First they gave a pair of words and asked what they had in common, easy ones like truck and train. Later they gave difficult pairs of words that seemed to have nothing in common, like acceptance and denial, but I was supposed to come up with a commonality anyway.

Finally, an interview. I remember the woman asking me if I knew what the saying, “What goes around, comes around” meant. I replied, “As you sow, so shall you reap” and she looked at me funny.

A seemingly endless time later my claim was denied and I got a lawyer to pursue it. By that time so much time had passed that I was coming out of the depression and was able to work a few hours a week. How much did I get paid per hour? he asked. “Thirty dollars,” I said, explaining that I could only work a very limited number of hours. It didn’t matter. As soon as I said thirty dollars the judge’s head would explode, evidently. Lawyer Joe recommended I drop the claim and I did. At least I was getting some work and some income even without disability.

It seemed that for me to get disability I would have had to be together enough not to need it, but sufficiently disabled that I would. Catch-22, as Joseph Heller said.


Inspiration and Mental Illness

high angle view of pencils on table

Photo by Pixabay on Pexels.com

I was manicky this week and it affected my blog writing. I had a post all ready to go this morning, but last night I thought about it and realized it was crap. It meandered, without focus. The ideas were confused. It sucked. So I got up this morning to write something different instead.

Many of you may recognize this aspect of mania or hypomania. You do something that you think is fantastic  while in the grip of mania and when you come down, you can’t see what you ever saw in it. Or you begin an ambitious project that you work on and work on but never can complete.

I was toying with the idea of “inspiration porn” – the sort of post or story or TV show that holds someone up as an ideal, usually because they’ve lost a bunch of weight and gotten themselves into shape, or have an illness or disability and managed to do – whatever – again. Think “The Biggest Loser.” Or amputees who’ve learned to eat with their feet. It’s put out there for entertainment and to make everyone feel good that whoever it is conquered whatever it was. It takes a regular person out of the context of their lives and reduces them to their condition. And the subtext is that if this brave person can become able to do or be whatever again, so can everyone else with the same problem.

It happened to a friend of mine who was at a gym on a treadmill. A woman came up to her and said how inspiring it was to see her working so hard to lose all that weight. “Excuse me?” was my friend’s reaction. She was doing it for herself, not for anyone else, and especially not to inspire some random stranger.

The thing is, there really isn’t any mental health inspiration porn. For one thing, it would make lousy TV. Oh, they’d get advertisers – all those purveyors of psychotropics that clog the airwaves. But who would watch a depressed person finally getting out of bed and taking a shower, unless she had a coach yelling at her?

Inspiration for those of us with mental health problems takes other forms. Celebrities who speak about their struggles with mental illness are one. They are inspiring because they break the taboo about talking about mental illness in public and because they have done so to help other people.

Then there are the superstars of mental health inspiration. Carrie Fisher, Glenn Close, and Jenny Lawson, to name a few. These are people who focus light on the difficulties and struggles of mental illness. Their communications don’t stop with the announcement that they have a condition and encouraging people to get treatment, though those are also good things. But the real inspirations are those who open their lives, take others with them through the journey of symptoms, treatments, relapses, small triumphs, and bigger successes. They speak and keep speaking and keep speaking their message. They don’t make the process sound easy, because it isn’t. And they speak with authenticity and authority because we know they’ve been there.

They do inspire us because they are honest and open, and they clearly care about helping others in the same proverbial boat.

We lost a true inspiration when we lost Mama Carrie. No one will ever really take her place. But you can tell that she was an inspiration by the many people whose life she touched and how they remember her. If someday they make a movie of her life, I hope it features not only her personal struggles, but all that she did for others. Her speaking and continuing to speak despite – or because – of her ongoing struggles.

We can carry on her work by doing the same, by shedding the stigma, by talking to others, even family and friends. Recently a friend “came out” to me that she takes an antidepressant and an anti-anxiety med (the same ones I take). I was proud of her, but I didn’t make a big deal of it. But I was impressed and pleased that she was able and willing to share even that much. She was saying that she was part of our tribe.

As Jenny Lawson reminds us, in this we are alone together. And that’s inspiring. 

Back to Work – Full Time

business clean computer connection

Photo by Ken Tomita on Pexels.com

As is true with many of us who can manage to work only part-time while dealing with bipolar disorder, I was always one paycheck away from financial disaster.

Then the checks stopped coming.

When my main source of work dried up, that financial disaster loomed closer. I knew that it was time to try to go back to regular work. Full-time. Outside in the world, if need be, rather than in my home office, in my jammies.

Looking for work was a job in itself (https://wp.me/p4e9wS-zY). It turns out I’m overqualified for many things and underqualified for others, sometimes both at once.

And the specter of bipolar reared its fearsome head. Even if I found full-time work, could I do it? Especially out there where it’s all people-y? It’s been years since I’ve worked in such an environment and my last few years at it did not go well, as I was beginning to slide into a major, long-lasting bipolar depressive episode.

Looking for work at home was not much better. Even telephone jobs (customer service or order handling, please, not sales) required some experience and my Girl Scout cookie days were back when we still thought it was safe to go door-to-door. When I responded to work-from-home jobs, many of them turned out to be Uber or Lyft, which is hardly the same as work-at-home, if you ask me.

I found a couple of small gigs to tide me over. Then I found one that was really promising.

Proofreader.

They warned me during the phone interview that I was vastly overqualified. I told them that this kind of job was exactly what I needed at this point in my life and please to keep me in mind if any of the other candidates washed out.

The job was with a transcription service, proofing scripts of meetings and reports that other people had typed up from audio files. But there wasn’t much of it, and it didn’t pay very well.

Then they asked me if I would move up to typing. And whether I would do it full-time.

Those were separate questions. I’m not a fast or good typist. I never took typing in high school (though I discovered that I needed it once I got into college). All these years I’ve been faking it, looking at the keyboard and using at most six or seven fingers to type with. But I said I’d try and I did. I’ve been sweating over these typing jobs and they take me lots longer than they do for other, ten-fingered, trained typists, but I’ve been hitting my deadlines.

Full-time was another issue. I said I’d try, with the understanding that I’d go back to part-time if I couldn’t handle it. It’s certainly been a challenge, forcing myself to spend six or more hours at the keyboard five days a week (and then using my days off to write blogs and work on my novel). It’s exhausting. But at least I’m still in my jammies and ready to go to bed afterward.

And I’ve learned a few things. One is “Never volunteer.” Often the company has extra work with even tighter deadlines that pay more per minute and are up for grabs. I made the mistake of grabbing a couple. It nearly did me in, combined with my regular work. (I did get an Amazon gift card for working on the Fourth of July.) Full-time work is hard enough. Full-time plus is a meat-grinder, or I should say a me-grinder.

So now for the big question – did I disclose my bipolar disorder?

I did not. As long as could do the work, it didn’t seem relevant. Work-at-home is not the sort of gig where they make accommodations or modifications for those with disabilities. And if I can keep up my stability and relative mental health, and get time off for doctor’s appointments, my mental status shouldn’t be relevant.

But I’m thinking I may have to cut back to four days a week. Five days is running me ragged. And then in December, when I retire, I can give it up altogether or work only a couple of days a week.

I will have a fixed income, which has both good and bad points, but at least it will lift from me the crushing anxiety of “Will we make the mortgage this month?” (I never was able to get disability.)

So, for now at least, and for the next few months, I will be working full- or almost full-time, if only my bipolar disorder will let me.

Wish me luck.

(Full disclosure: That photo is not an actual representation of my writing space. Mine is littered with legal pads, stuffed animals, Kleenex, and water bottles.)

Reaching Out and Reaching In

A lot has been said in recent days about reaching out when you’re in trouble psychologically. And that’s always a good idea. Reach out to your friends, your family, your therapist, your psychiatrist, your church or synagogue or temple.

hands people friends communication

Photo by Pixabay on Pexels.com  

Unfortunately, not everyone has those resources. And sometimes when you reach out to them, they do not reach back to you or even respond in hurtful ways.

Sometimes – many times – you’re just not able to reach out. That’s true of me, anyway. When major depression hits me like a truck, I get immobilized. Uncommunicative. Isolated. I usually have the wherewithal to get to my therapist, if my husband drives me, but not much more.

My family and friends can tell when I’m in trouble. And they do reach out, even when I don’t reach back.

My mother always knew when I hit a particularly bad spot because she could recognize it in my voice – it lacked animation, even if I was talking about something I loved. Not that I talked much or felt much. Depression can damp down all your feelings sometimes. You don’t cry, you don’t feel sad. You feel nothing. And it shows to someone who knows how to look and listen.

This is called “flat affect” by psychiatrists. The person’s face, voice, mannerisms do not reflect emotions, sometimes not even anxiety or despair. And sometimes people adopt a flat affect so as not to betray their inner turmoil. (It can still leak out around the eyes, even to relative strangers. And I don’t mean crying.)

My husband knows I’m depressed when I turn monosyllabic. Ordinarily, I enjoy talking to my husband about anything and nothing – things we’ve read or heard, what’s happening at work (his, mostly), funny things the cats did, and so forth. But when I stop responding and communicating, or respond only with “yeah,” “nah,” and “meh” sorts of answers, or don’t laugh or at least groan at his jokes, he knows I’m headed downward.

I stop communicating other ways, too. I don’t post on Facebook or only pass along the occasional pass-along. I skip commenting on posts regarding things I usually care about. I spend hours alone reading, if my sometimes-dubious powers of concentration let me. Or I sleep, and nap, then sleep some more. I certainly don’t leave the house or even make plans to go out. I don’t call friends. I isolate. I don’t reach out, like the memes say I’m supposed to.

I am fortunate to have friends that do reach out to me. John would lend me books, talk about them with me, and listen if I needed to vent. Peggy would call and invite me to visit, even when she knew I wasn’t leaving the house. Pete sometimes IM’s every day just to check in and JB assures me that when he IM’s and I don’t feel like chatting that’s still okay. Robbin calls me and tells me all about her life even when I can’t talk about mine, then says, “Let me know when you surface.” If she doesn’t hear from me for awhile, she calls again and reminds me that I can call her too. (She can also “read” my voice and knows when there’s some topic I’m avoiding.) My husband offers a hug or kisses me on the head. My mother prayed for me. I am fortunate indeed to have had people like these around me when I really need them.

Reaching out to others is good. So is reaching in to the suffering. Best is a combination of both. But that takes work and not everyone is able to do it.

If you can reach out, reach out.

If you can reach in, reach in.

If you’re lucky, you’ll meet in the middle, where hope lives.



